
BPC-157: what does the human evidence show?
BPC-157 affects processes involved in repair in laboratory and animal studies. Human studies, however, have not reliably shown that it helps injuries heal or established its risks. Small clinical reports and a larger analysis of medical records describe mixed experiences; a registered hamstring trial has no posted results. Understanding what each study measured helps distinguish a promising research idea from a demonstrated treatment.

What BPC-157 is—and why researchers study it
BPC-157 is a synthetic peptide: a short chain of 15 amino acids, the building blocks of proteins. It has attracted attention because laboratory and animal experiments suggest effects on processes involved in repair, including how cells move into damaged tissue and how small blood vessels form. Those observations make it a research candidate. They do not yet establish a treatment that reliably heals human tendons, muscles, joints, or the gut. [1] [13] [14]
The human evidence is small and uneven. It includes a knee-pain report, a bladder-symptom pilot, a two-person safety report on infusion into a vein, an older conference summary of a trial in ulcerative colitis (an inflammatory bowel disease), and a recent analysis of clinical notes. A registered trial in hamstring injuries, affecting muscles at the back of the thigh, proposes to test recovery more directly but has no posted results. [1] [2] [3] [4] [5] [11]
Commercial context matters when reading this evidence. In the knee report, patients paid for the peptide and injection; the authors declared no conflicts of interest. The authors of the clinical-note analysis reported employment by the data-analysis company nference. These are disclosed relationships, not reasons to discard the findings. They help readers understand how the evidence was produced and why an independent comparison would be valuable. [2] [5]
Less pain, better function, and repaired tissue are different outcomes.
A person can feel better without a damaged tendon or cartilage being restored. A useful healing trial therefore asks several questions: Did symptoms improve? Could people return safely to ordinary activity or sport? Did a relevant examination or scan show structural recovery? Comparing those outcomes with an appropriate control group helps separate a treatment effect from natural recovery, rehabilitation, and expectations.
What the laboratory findings actually show
Repair requires coordinated activity. Cells must survive injury, move into the damaged area, and help rebuild its structure. New blood vessels can support this process by supplying oxygen and nutrients. A substance that changes one of these steps in a dish or an animal may deserve further study, but successful repair in a person depends on the whole process.
A 2011 study examined rat tendon cells and tendon tissue maintained outside the body. BPC-157 increased cell outgrowth, movement, and survival under an experimental stress. It did not directly increase the rate at which the cultured tendon cells multiplied in the test used. The researchers linked the findings to signals involved in cell movement and attachment. This is evidence about cellular behavior, not a clinical demonstration that an injured human tendon heals faster. [13]
A 2026 study added a proposed molecular explanation for blood-vessel effects. In cultured human blood-vessel lining cells, BPC-157 interacted with a protein called FBXO22, slowing the breakdown of BACH1, a protein that helps control gene activity. This was associated with cell growth and vessel formation. The researchers also studied injuries in rodents. “Human cells” here means cells grown in the laboratory, not patients treated with BPC-157. The study helps refine a possible mechanism; it does not supply a human benefit or safety estimate. The team also described an earlier patented synthesis method and development of an injectable BPC-157 product; the authors declared no competing interests. [14]
Product identity also matters. The US Food and Drug Administration (FDA) reviewed two chemical forms of BPC-157, called the free base and acetate, while older reports do not always characterize the chemical form adequately. An injection into a knee, an injection around bladder tissue, an intravenous infusion, a rectal enema, and an oral product expose the body differently. Findings from one preparation and route cannot simply be transferred to another. [1]
The small human studies, side by side
Report | What was studied and reported | What the result can tell us |
|---|---|---|
Knee pain, 2021 | Seventeen patients were identified and 16 reached by telephone. Twelve received BPC-157 alone; 11 reported improvement and one did not. Seven of the 12 reported relief lasting six months to one year. Four received a combination described as BPC-157 plus thymosin beta-4; three reported improvement and one did not. | A small uncontrolled record of patients' experiences. It does not establish tissue regeneration or distinguish treatment effects from other explanations. [2] |
Bladder symptoms, 2024 | Twelve women aged 39–76 with interstitial cystitis, a condition causing bladder pain and related symptoms, received injections around inflamed bladder areas during cystoscopy, an examination of the bladder with a viewing instrument. Ten reported complete symptom resolution and two substantial improvement. The published summary reported no adverse events. | An encouraging symptom report from a selected group, without a comparison group. The published summary does not state how long the women were followed, leaving the persistence of relief unclear. [3] |
Intravenous safety pilot, 2025 | Two adults, a 58-year-old man and a 68-year-old woman, had both previously received intravenous BPC-157. During three days of monitoring, the report described no reported side effects or measured changes in selected laboratory measures. | A very limited short-term observation in two previously exposed people. It cannot establish general safety or detect uncommon and delayed harms. [4] |
Ulcerative colitis, 2005 conference summary assessed by FDA in 2026 | Fifty-three participants were randomly assigned to receive BPC-157 as an enema or placebo (a preparation without BPC-157) for two weeks; 46 completed the study. Disease-activity scores improved more numerically with BPC-157, but the reported confidence interval for the between-group difference included no difference. | A controlled comparison, but incompletely reported and not a convincing demonstration of benefit in FDA's assessment. FDA's assessment was based on a short conference summary with too little detail to establish the treatment's benefit or safety. [1] |
The knee study is often relevant to injury discussions, but its design deserves attention. Patients had several kinds of knee problems, treatment was not randomly assigned, and the follow-up depended on telephone reports. There was no untreated or placebo group and no objective demonstration of newly repaired cartilage or other tissue. Some patients had scans before treatment, which is different from demonstrating repair with a planned follow-up assessment. Combining two peptides in four patients also prevents attributing their experiences to BPC-157 alone. [2]
The bladder pilot concerned women whose symptoms had not improved with pentosan polysulfate, a medicine used for this bladder condition. It studied a procedure in a specific condition, not general injury recovery. The two-person infusion study addressed selected short-term observations, not whether treatment helped any disease. These differences explain why pooling the reports into one apparent success rate would be misleading. [3] [4]
The ulcerative-colitis result needs a little statistical translation. A confidence interval expresses the uncertainty around an estimated difference. The interval reported in FDA's account, −4.84 to 1.62, crossed zero: the data were compatible with no difference between the groups. FDA also described incomplete reporting and unclear endpoint definitions. Three BPC-157 participants and two placebo participants withdrew because of adverse events, described mainly as progression of ulcerative colitis; one person in each group was lost to follow-up. Those withdrawals belong in the evidence alongside the numerical symptom improvement. They do not, by themselves, establish that BPC-157 caused worsening. [1]
What the larger 2026 clinical-note analysis adds
A September 7, 2026 preprint examined records containing documented BPC-157 use in 1,039 people. A preprint is a publicly shared manuscript that has not yet completed peer review. The researchers used an AI language model to extract information from clinical notes; a clinician checked samples of the extracted information at one participating site. [5]
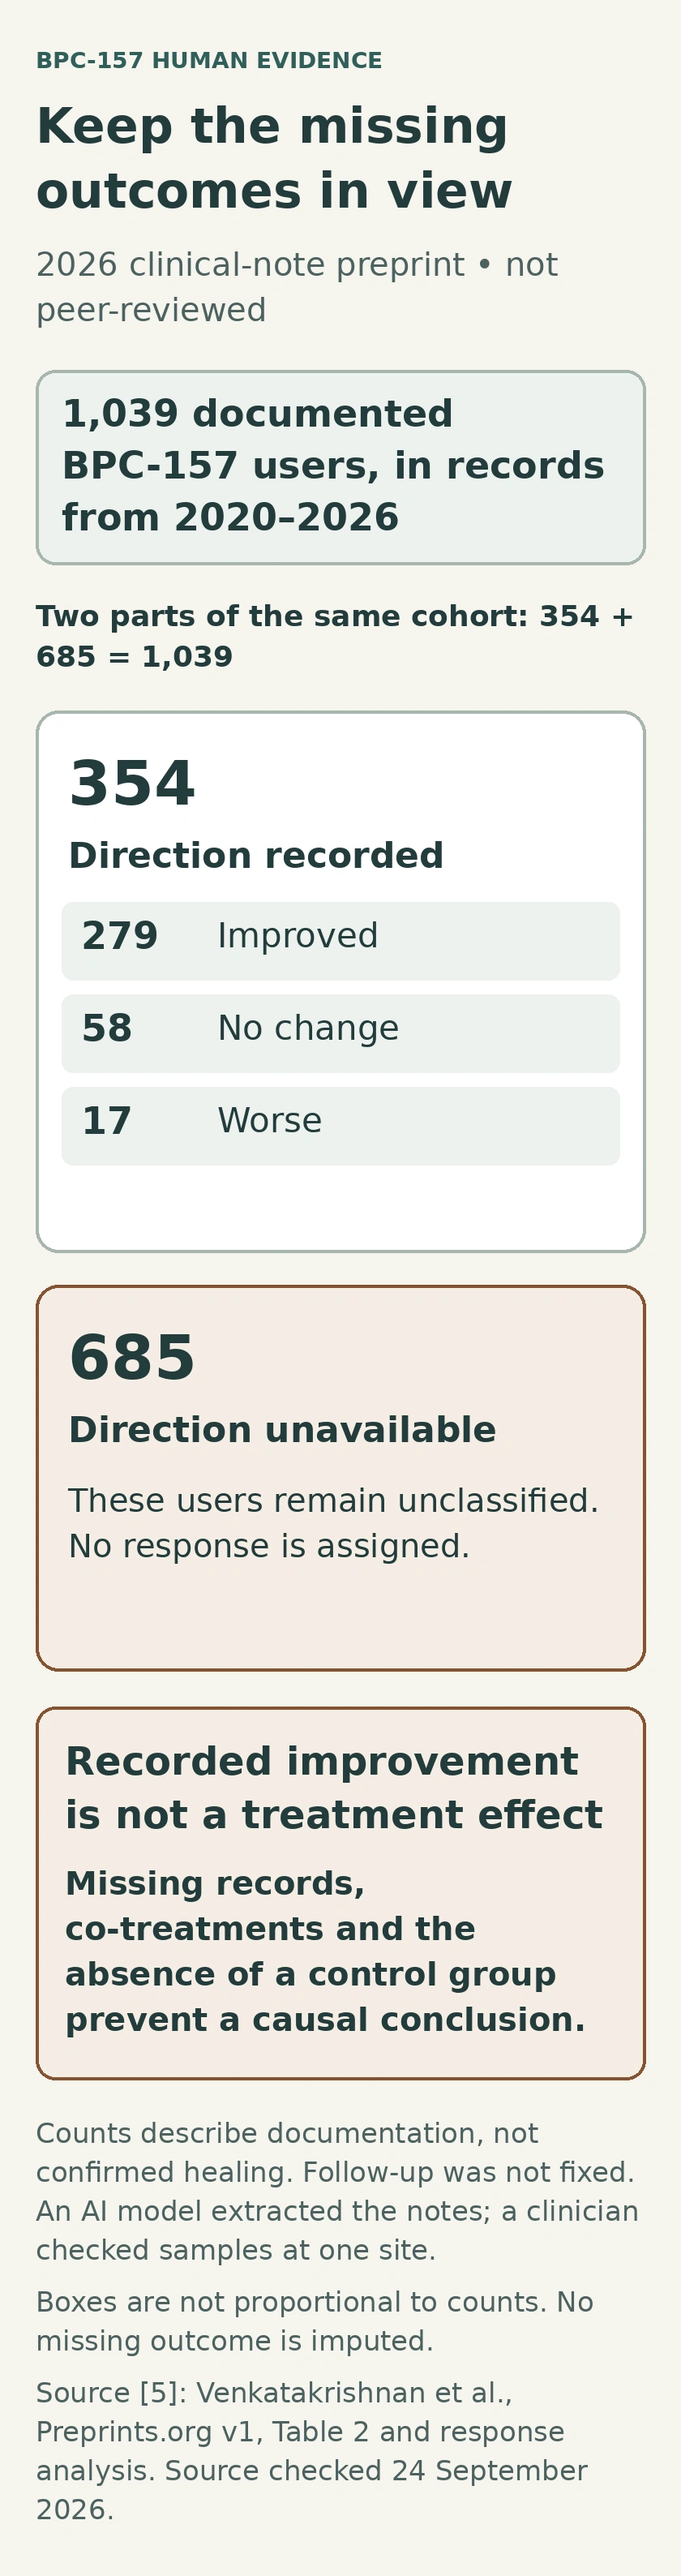
Recorded change in symptoms | Number of people |
|---|---|
Improved | 279 |
Unchanged | 58 |
Worsened | 17 |
No information on whether symptoms changed | 685 |
Total documented users | 1,039 |
The first three rows add up to 354 people with a recorded direction of change. The 685 people without that information must remain missing outcomes; they cannot be counted as successes or failures. Even among the 354, improvement recorded after use does not establish improvement caused by use. There was no comparison group, and approximately half of the users had other therapeutic agents recorded. Dose, route, duration, and follow-up were not standardized. Clinical-note extraction can also miss or misclassify information despite checking. [5]
Among 129 people whose notes confirmed that they had stopped BPC-157, adverse effects were the recorded reason in 24. That is a reason to investigate the experiences, not a dependable adverse-event rate: exposure and reporting were incomplete, other agents could contribute, and the analysis was not designed to capture every event. The study is useful evidence that people are using BPC-157 and reporting mixed experiences. Its larger head count does not overcome the absence of a controlled comparison. [5]
A registered trial asks a more specific question
The registered hamstring study is a phase 2 trial, intended to test possible benefit and further assess safety. It proposes to compare BPC-157 with placebo, with the same rehabilitation program in both groups. Participants would be assigned by chance, and neither they nor the people assessing recovery would know which treatment they received. The plan is to enroll 120 adults aged 18–45 with a recent grade II hamstring injury confirmed by magnetic resonance imaging (MRI). The main planned outcomes are return to unrestricted sport through eight weeks and change in the volume of injured tissue on MRI at day 14. Measuring return to activity and changes in injured tissue separately could help show whether treatment makes a meaningful difference. [11]
The sponsor, Hudson Biotech, listed recruitment in Shenzhen, China, in the registry entry updated on February 27, 2026. The entry contains no posted results. A recruitment listing and a study plan do not show that participants recovered faster or experienced fewer harms; those questions require results from the trial. [11]
If a well-conducted trial eventually reports a meaningful benefit, it will still matter which patients, preparation, route, comparator, and follow-up produced it. One positive injury trial would answer that defined question, rather than establish every claimed use.
Safety has several separate parts
One question concerns what the molecule does to the body. Another concerns what is actually in a particular preparation. FDA identifies potential immune reactions, peptide-related impurities, and difficulties adequately characterizing the active ingredient, together with limited safety information for proposed routes. An immune reaction means that the body's defenses recognize and respond to the administered material; product identity and purity are separate quality questions. [1] [6]
FDA also identified possible safety signals in studies in which rats and dogs received BPC-157 free base by injection into muscle for 28 days. These included changes in blood-clotting tests and liver-associated blood measurements. The study authors had interpreted the changes as incidental, while FDA considered them potentially important. FDA noted that longer studies were unavailable to show whether the findings would recur or additional problems would emerge. These animal findings call for further investigation; they do not establish a rate of harm in people. [1]
Route and duration add further questions. A few days of blood tests cannot reveal what months of exposure might do, and a preparation placed locally does not establish the safety of intravenous use. The small human reports provide too few observations to estimate uncommon harms reliably.
Cancer claims require particular care. FDA's 2026 review found no studies determining the carcinogenic potential of the reviewed BPC-157 forms. Laboratory effects on blood-vessel growth do not establish that BPC-157 causes cancer in people; nor do short reports without detected problems establish cancer safety. The available material does not provide a reliable human cancer-risk estimate. [1]
US regulation and sport rules answer different questions
An FDA advisory discussion is not approval of a medicine. The July 23, 2026 Pharmacy Compounding Advisory Committee agenda concerned BPC-157 free base and acetate for ulcerative colitis. It was not an evaluation approving injury recovery or longevity treatment, and the committee's advice is nonbinding. Compounding—preparing a medicine by combining or changing ingredients for a medical need—has its own legal conditions; consideration of an ingredient under that framework does not approve a finished medicine. These are US distinctions, not a determination of access in another country. [1] [8] [12]
“Off-label” has a different meaning: an already approved drug is used outside its approved labeling. Calling an unapproved BPC-157 preparation off-label does not give it the evidence or regulatory status of an approved product. [9]
For athletes subject to anti-doping rules, the World Anti-Doping Agency's (WADA) 2026 Prohibited List expressly names BPC-157 in S0, its category for non-approved substances, and prohibits it both in and out of competition. The US Anti-Doping Agency (USADA) describes permission to use it for medical reasons—a therapeutic-use exemption—as unlikely, while noting that applications are considered individually. A prescription is not an automatic exemption; athletes should check with the organization responsible for their rules. [7] [10]
Questions that make a treatment discussion more useful
What is the diagnosis and expected course? A tendon tear, joint arthritis, muscle strain, and bladder pain are different problems with different established care options.
What is the proposed goal? Less pain, better function, faster return to sport, and structural repair should be measured separately.
Which study matches the proposal? Check the chemical form, product, route, condition, and patient group—not just the name BPC-157.
What explains the apparent improvement? Ask whether the study compared treatment with placebo or usual care, and whether rehabilitation or other therapies differed.
What follow-up would detect harm or lack of benefit? Short laboratory monitoring and informal symptom reports leave substantial gaps.
Which rules apply? Product regulation, the local supply framework, and sport eligibility are distinct questions.
BPC-157 has biologically interesting research behind it and limited human observations worth studying further. The unresolved step is demonstrating, in dependable controlled studies, that a defined preparation produces a useful patient benefit with an adequately characterized safety profile.
What remains uncertain
Most human reports lack a comparison group, and some do not say how long participants were followed. The older ulcerative-colitis study has too little reported detail for a firm conclusion. Many outcomes are missing from the medical-record analysis, and the investigators checked only samples of the AI-extracted data, so recording errors are also possible. The planned hamstring trial has not provided results. These gaps leave the size of any benefit, uncommon harms, and long-term safety uncertain; findings from one preparation or route cannot establish the effects of another.
References
- FDA Evaluation of BPC-157-related bulk drug substances
- Lee and Padgett: Intra-Articular Injection of BPC 157 for Multiple Types of Knee Pain
- Lee, Walker and Ayadi: Effect of BPC-157 on Symptoms in Patients with Interstitial Cystitis
- Lee and Burgess: Safety of Intravenous Infusion of BPC157 in Humans: A Pilot Study
- Venkatakrishnan et al.: Rising Use of Unapproved BPC-157 and Associated Patient-Reported Outcomes Curated from Clinical Notes
- FDA Certain Bulk Drug Substances for Use in Compounding that May Present Significant Safety Risks
- USADA BPC-157: What Athletes Should Know About the Prohibited Experimental Peptide
- FDA July 23–24, 2026 PCAC meeting
- FDA Understanding Unapproved Use of Approved Drugs Off Label
- WADA 2026 Prohibited List
- ClinicalTrials.gov NCT07437547: BPC 157 for Acute Hamstring Muscle Strain Repair
- FDA Bulk Drug Substances Used in Compounding Under Section 503A of the FD&C Act
- Chang CH et al. The promoting effect of pentadecapeptide BPC 157 on tendon healing involves tendon outgrowth, cell survival, and cell migration. Journal of Applied Physiology, 2011.
- Zhang J et al. BPC157 drives angiogenesis through FBXO22-dependent stabilization of BACH1. Cell Communication and Signaling, 2026.
Disclosure
Prepared with AI assistance.