
Partial reprogramming: what the eye trial can tell us
Partial reprogramming has reached human testing. ER-100’s sponsor announced first dosing in June 2026, in an eye-disease study planning 18 adults. The trial asks first about safety; whether it improves useful vision remains unanswered. Mouse experiments provide a scientific rationale, but the human evidence dated September 21, 2026 contains no reported outcomes showing restored sight or broader rejuvenation.
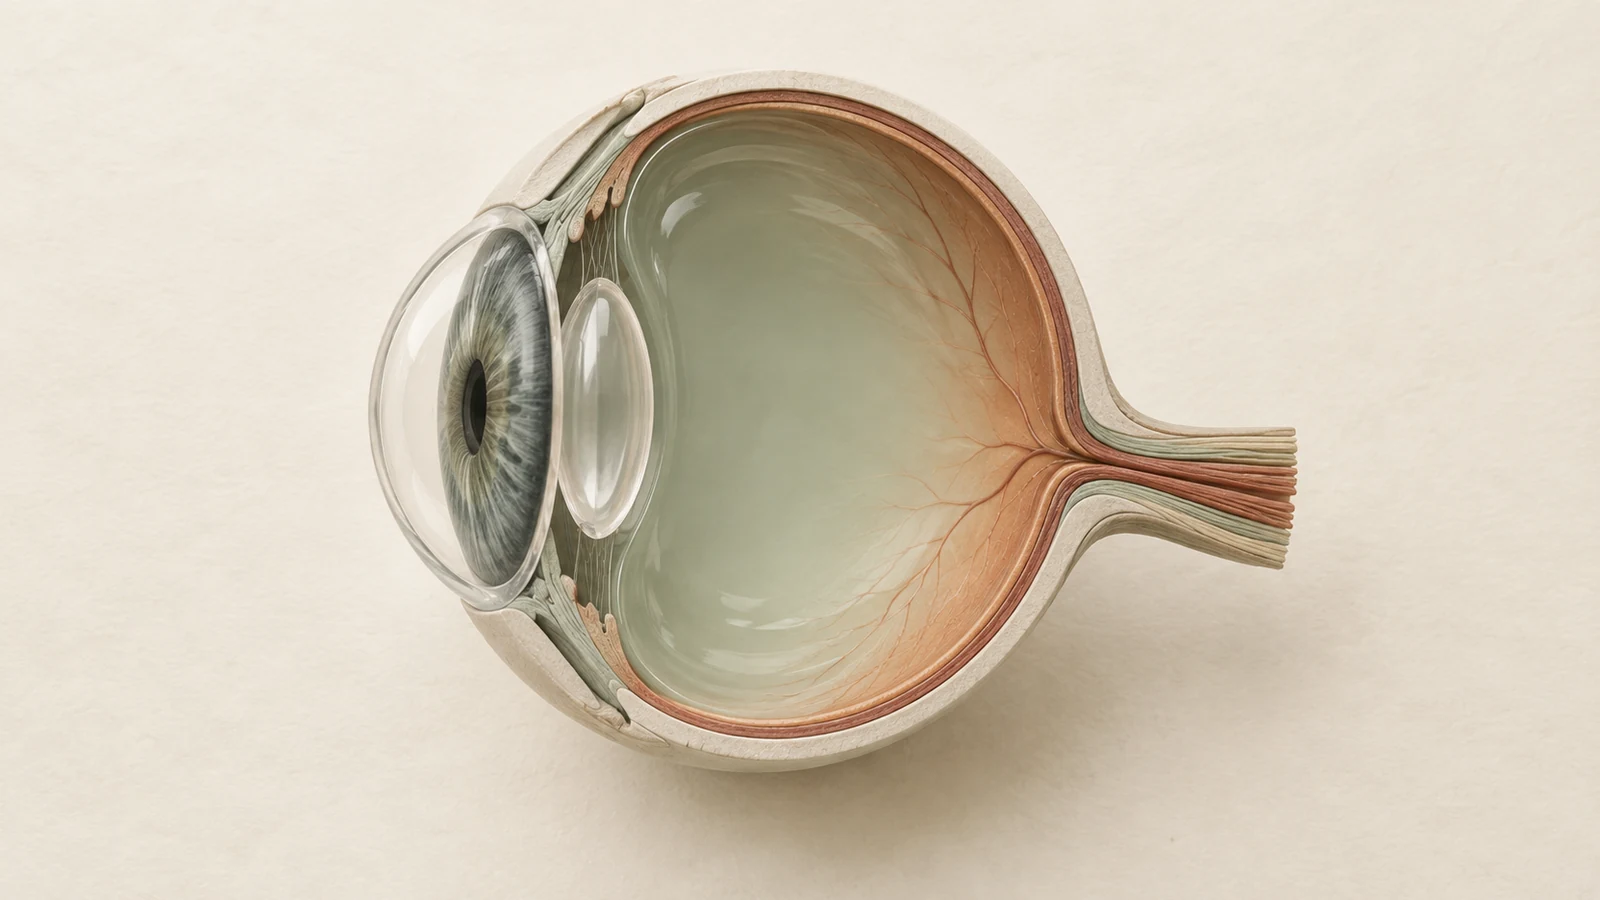
Life Biosciences’ ER-100 tests a concrete idea: can changing gene activity help damaged nerve cells in the eye while preserving their specialized role? Its first human study is a meaningful step for partial reprogramming. The experiment’s value depends on what happens to the participants, including unwanted effects, rather than on the label “rejuvenation.” Evidence and trial-status information here are dated September 21, 2026. [1] [2]
What is known—and what the trial must establish
Shown: the sponsor announced first dosing on June 9, 2026, and a Phase 1 protocol describes safety and visual assessments in adults with optic-nerve disease. Earlier mouse experiments reported nerve-fiber regeneration and improved visual-function measurements. [1] [2] [5]
Not shown: restored human vision, long-term human safety, or rejuvenation of the whole body. The registry contains no posted results. [1]
What would change the assessment: a complete report of treated participants, observed harms, and visual outcomes, followed by controlled testing if early findings justify it. A useful eye treatment would be an important result even without a broader longevity effect. [1] [4]
How partial reprogramming is intended to work
A nerve cell and a skin cell largely carry the same genetic instructions, but use them differently. The epigenome is part of the system that regulates which genes are active. It includes chemical marks and associated machinery; changing this regulation need not change the underlying DNA sequence. [3] [5]
Reprogramming factors are proteins that can alter a cell’s pattern of gene activity. Full changes in cell identity are not the aim here. Partial reprogramming seeks to recover selected functions associated with younger cells while keeping the specialization that makes the cell useful. In the retina, a younger-looking molecular measurement is insufficient if the cell no longer works as a nerve cell. [1] [3] [5]
ER-100 supplies instructions for three factors: OCT4, SOX2, and KLF4, abbreviated OSK. An engineered adeno-associated virus, or AAV, carries the instructions into retinal cells. A drug-controlled system is intended to regulate when the cells produce OSK. That control is part of the treatment design; investigators still need to monitor the delivery system and the cells it affects. ER-100 is a specific experimental gene therapy, with a defined product and target tissue. [1] [3]
“Partial” describes the intended degree of reprogramming. The word is not a safety guarantee. The amount, location, and duration of the changes must prove appropriate in the cells actually exposed.
The human study: 18 planned participants, no reported outcomes
The registered study, NCT07290244, plans to enroll 18 adults: 12 with open-angle glaucoma and six with non-arteritic anterior ischemic optic neuropathy, usually shortened to NAION. Both conditions damage the optic-nerve pathway, which carries information from the eye toward the brain. Glaucoma is a chronic disease; NAION involves injury associated with impaired blood supply. Evidence of benefit in one group would not automatically establish benefit in the other. [1] [2]
This Phase 1 study is nonrandomized and open-label: treatment is not assigned by chance between comparison groups, and participants and investigators know it is being given. Measurements are compared with each participant’s starting point. That design can reveal early safety findings and signals worth investigating, but it has limited ability to determine whether treatment caused an improvement. [1] [4]
Study feature | What it means for interpreting a result |
|---|---|
Sequential treatment groups, with independent safety review before proceeding | Investigators plan to learn about risks before exposing later groups. This is a safeguard, not an observed safety result. |
Primary assessments through days 56 and 112, including adverse events, laboratory tests, and eye examinations | The first question is whether concerning early changes emerge. Some visual measurements also contribute to exploratory assessments of benefit. |
Measures of visual function and retinal structure | These can identify possible effects. A better scan or electrical response is not identical to better use of vision in daily life. |
Follow-up planned for up to five years | The protocol recognizes the need for longer observation. It does not yet provide five years of safety evidence. |
All of these features come from the protocol. Planned enrollment and follow-up should not be read as completed observations. [1]
The registry update is dated May 19, 2026, while its field confirming recruitment status is dated March 2026. It lists the study as recruiting, but neither date establishes live site capacity or a place for an individual patient. No results are posted in this dated record. [1]
Three dates describe different milestones
The sponsor’s pipeline page dates US Food and Drug Administration (FDA) authorization to proceed to January 15, 2026. Life Biosciences publicly announced clearance of the investigational new drug application on January 28. It then announced first dosing on June 9. The first two dates concern permission to conduct research and its announcement; neither is a marketing approval or a result showing benefit. [2] [3] [8]
The FDA describes Phase 1 as a stage for learning about safety, exposure, and dosing. Larger studies are generally needed to establish benefit and characterize less common harms. An encouraging early finding could justify further research without establishing a treatment-launch date or suitability for healthy adults. [4]
Why researchers chose the eye
The eye offers a defined treatment site and several ways to measure structure and function. The sponsor contrasts this relatively compartmentalized setting with an organ such as the liver, which interacts extensively with the rest of the body. That is a rationale for a first study, not proof that eye delivery eliminates local or systemic risk. [3]
It helps to distinguish delivery, biological response, and patient benefit. Getting the instructions into a cell does not show that the cell responds as intended; an intended cellular response does not by itself show that the patient sees better. Even within visual testing, an electrical response, a retinal image, and useful everyday sight describe different outcomes.
A credible account will therefore report the measurements specified before the study began, the size and consistency of changes, and whether findings differ by diagnosis. Selecting the most favorable measurement after seeing the data would give a less reliable picture of what the treatment does. [1] [4]
What the mouse studies contribute
In their 2020 mouse study, Lu and colleagues reported nerve-fiber regeneration and improved visual-function measurements after OSK expression in mouse retinal ganglion cells—the nerve cells whose fibers form the optic nerve. They studied injury, experimental glaucoma, and aging models, and linked the response to cellular machinery that changes chemical marks on DNA, called DNA methylation. These findings provide a reason to test the approach in people. [5]
They do not predict how much useful sight a person with years of optic-nerve damage might recover. Species, injury models, delivery conditions, and visual tests differ. A favorable eye experiment also cannot establish that the same intervention can safely improve the heart, brain, or whole body. [5]
The term “rejuvenation” needs that context. In a study it may describe a molecular pattern or one cellular function. A reader may hear a promise of comprehensive restored health. The actual measurement is what determines the finding’s meaning.
The main safety question: useful repair without unwanted cell changes
Reprogramming can change cell behavior profoundly. Researchers need to determine whether repair can be separated from unwanted loss of cell identity or abnormal growth.
A different mouse system shows why this matters. Ohnishi and colleagues found that incomplete exposure to four reprogramming factors could produce tumors through altered epigenetic regulation. Their factor combination and experimental setting differed from ER-100. The result cannot quantify ER-100’s cancer risk, but it shows why stopping short of full reprogramming is not a universal guarantee of safety. [6]
The favorable animal observations matter too. Lu and colleagues reported no increase in tumors under the OSK conditions they tested, including prolonged expression. That is relevant reassurance within those experiments. It cannot exclude uncommon or delayed harm in humans, or erase differences in delivery and tissue between experiments. [5]
ER-100’s three-factor design and controlled expression must therefore be evaluated as the specific product they are. A feature intended to reduce a hazard needs evidence that it works. Relevant findings include unwanted eye changes, immune responses, other adverse events, and problems emerging after treatment has ended. [1]
US FDA guidance on gene therapy explains that delayed adverse events can require extended observation, depending on the product’s risk assessment. An early statement that a treatment was tolerated needs the number of people treated, how long they were actually followed, and a description of what investigators monitored. A small group with no observed event cannot rule out an uncommon event. [7]
Changing gene regulation without deliberately editing DNA also does not make the intervention biologically minor. Substantial effects and risks can arise without cutting or replacing a DNA sequence. [5] [6]
How Healthy Longevity Clinic experts evaluate the evidence
For a person worried about losing vision, the decisive question is whether an intervention can preserve or restore useful sight at an acceptable risk. HLC’s interpretation separates that goal from a younger molecular profile. An effect on gene activity can support the biological hypothesis; it cannot substitute for a visual benefit that matters to the patient. [1] [5]
The first human study should be judged by what it can reasonably establish. With 18 planned participants, two different diagnoses, no randomized comparison, and open-label observation, a promising change would justify careful follow-up rather than an immediate conclusion about effectiveness. HLC would give particular weight to consistency across relevant visual measures, the outcome in each diagnosis, and complete reporting of adverse events and withdrawals. Baseline changes can also reflect measurement variability, other care, disease course, or expectations. [1] [4]
For a clinical conversation, this means keeping existing eye care and a research decision as distinct questions. Ask whether the trial addresses your diagnosis, what participation would require, and how delayed effects would be monitored. A complete early safety report could strengthen the case for the next trial. A controlled, durable improvement in meaningful vision outcomes would change the assessment of benefit. Neither result alone would establish general rejuvenation in healthy adults. [1] [4] [7]
What a useful first report needs to contain
A Phase 1 report should show how many people actually received treatment, their diagnoses, results by treatment group, and how long they were observed. It should explain withdrawals and report adverse events both suspected to be treatment-related and judged unrelated. Those details make a safety statement interpretable. [1] [4]
If vision improves, a later randomized comparison with participants or assessors unaware of treatment assignments, when feasible, can address alternative explanations that this initial study cannot settle. Transparent reporting of a disappointing result would also be useful: it could narrow the hypothesis without ruling on every form of reprogramming.
Three questions for an ophthalmologist or study team
Which safety and visual outcomes is this trial primarily designed to measure, and how do they relate to my diagnosis?
How would participation interact with my existing care, and what follow-up or reasons to pause treatment should I understand?
What is still unknown about delayed effects, and when and where will complete results—including unfavorable findings—be reported?
Common questions
Has partial reprogramming been tried in people?
Life Biosciences announced that the first ER-100 participant was dosed on June 9, 2026. The dated registry describes the human study, but contains no posted outcomes. First dosing establishes that the experiment has begun, not what its answer will be. [1] [2]
Does using only three factors remove the cancer concern?
No human result here establishes that. The different mouse experiments contain both adverse findings with four factors and reassuring observations under tested OSK conditions. Neither supplies a numerical cancer-risk estimate for ER-100 in people. [5] [6]
Does the planned five-year follow-up show that it is safe for five years?
No. A planned observation period states what investigators intend to do. Safety evidence depends on how many participants have actually been observed, for how long, and what happened. [1] [7]
Would better vision prove that aging had been reversed?
It could establish a valuable disease-specific benefit if supported by an adequate study. The conclusion would concern vision; effects on other organs would require their own studies. [1] [4] [5]
What remains uncertain
A small study comparing participants with their own baseline can identify early signals but cannot confidently establish efficacy or exclude uncommon delayed harms. Different mouse factor combinations, tissues, and delivery systems cannot be used to calculate ER-100’s human cancer risk. Both the adverse four-factor findings and favorable OSK observations have limited applicability. Recruitment status and follow-up are plans or dated administrative descriptions, not live capacity or completed safety evidence. Sponsor-reported US authorization to begin testing is distinct from marketing approval.
References
- Evaluating ER-100 for Safety in People With Glaucoma or Non-Arteritic Anterior Ischemic Optic Neuropathy
- First Patient Dosed in Phase 1 Trial of ER-100 for Optic Neuropathies
- Pipeline
- Step 3: Clinical Research
- Reprogramming to recover youthful epigenetic information and restore vision
- Premature termination of reprogramming in vivo leads to cancer development through altered epigenetic regulation
- Long Term Follow-up After Administration of Human Gene Therapy Products
- FDA Clearance of IND Application for ER-100 in Optic Neuropathies
Disclosure
Prepared with AI assistance. Life Biosciences sponsors the human trial and issued the milestone announcements. Several authors of the 2020 mouse study disclosed relevant company equity, advisory roles, and patents, including interests connected with Life Biosciences. These relationships make complete methods, unfavorable findings, and independent replication particularly important. [1,5]