
Thymus regeneration: what TRIIM found
TRIIM, supported by Intervene Immune, reported improved thymus imaging in seven of nine men after a year of treatment, alongside selected immune and DNA-age changes. The study had no untreated control group. Healthy Longevity Clinic examines the promise of thymus regeneration for immune health and why the next decisive evidence should concern useful immune function, fewer serious infections and safety.
Longevitytech.fund portfolio · Intervene Immune
Intervene Immune is a Longevitytech.fund portfolio company. We are proud to support research into thymus regeneration and the prospect of maintaining immune function as we age. [9]
The appeal of thymus regeneration is practical: a more capable immune system could help people stay well as they age. TRIIM explored whether a combination including growth hormone could change an aging thymus and related blood measurements. Its results support a research hypothesis. The next question is whether those changes produce worthwhile health benefits with acceptable risks. This article reflects evidence dated September 22, 2026. [1]
What is shown, and what remains open
Shown: a small human pilot reported changes in thymic imaging, selected immune-cell measures, and methylation-clock estimates. Some immune measures did not improve consistently. [1]
Not shown: that the combination prevents clinically important infections or cancer, or is suitable for routine preventive treatment. An uncontrolled study cannot establish the size of a treatment effect. [1]
What would change the assessment: complete results from a controlled comparison, followed by evidence of useful immune function, durable clinical benefit, and adequate safety follow-up.
Why the thymus matters
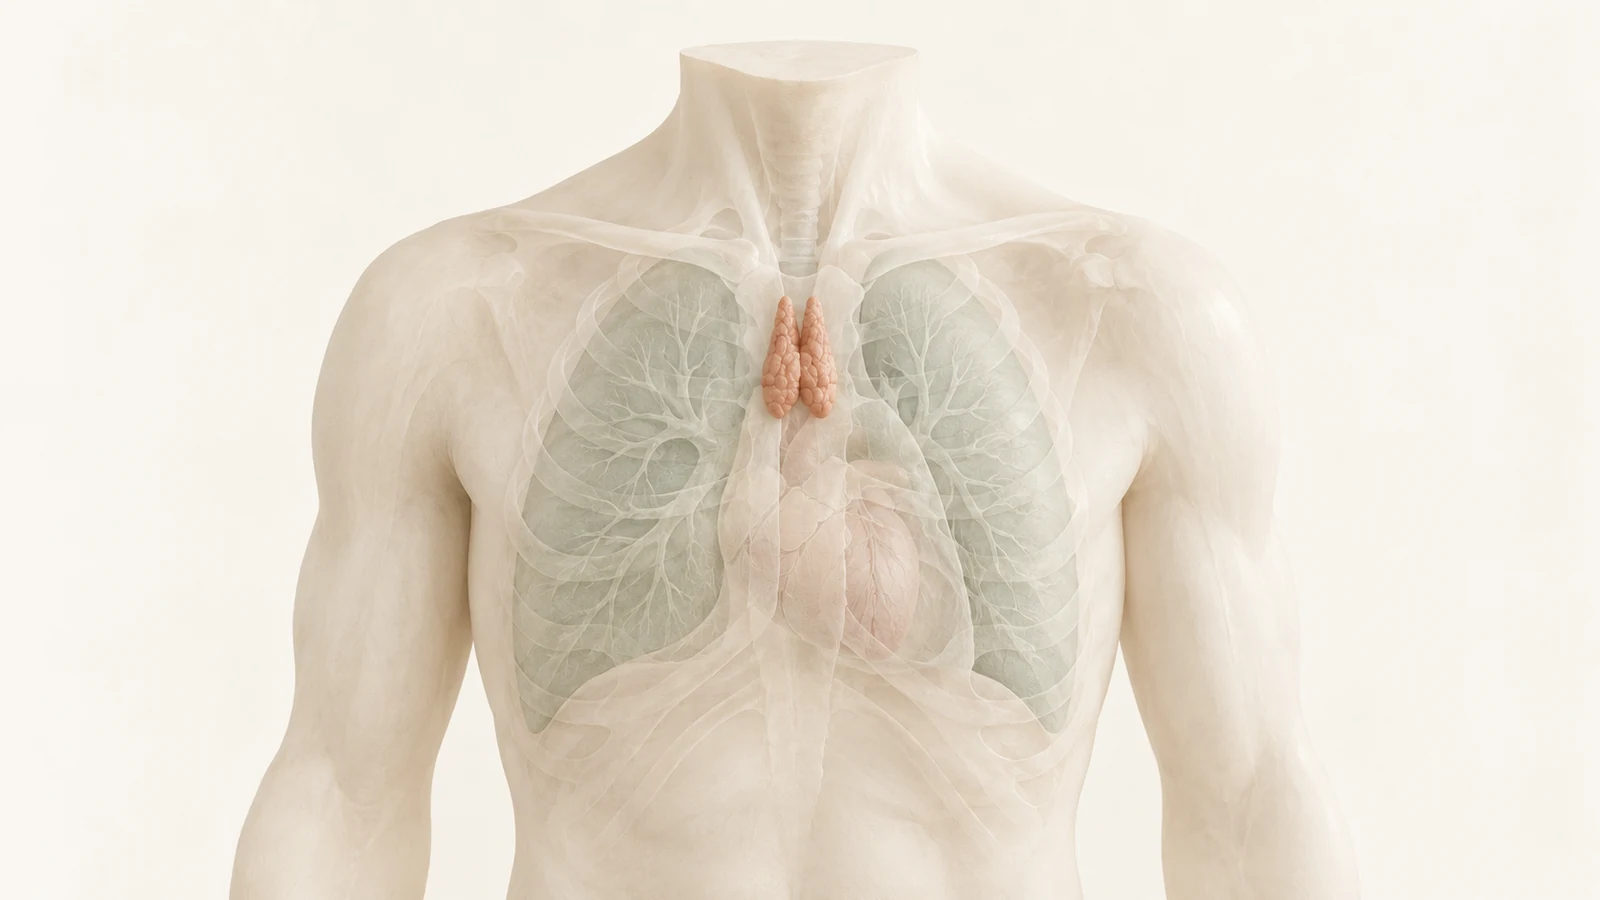
The thymus is an organ where developing T cells mature. T cells help the immune system recognize and respond to threats. With age, active thymic tissue is progressively replaced by fat, although some capacity remains in adulthood. Restoring useful activity is therefore a plausible goal. [2]
A better-looking scan is only part of that goal. Newly produced T cells would need to expand the range of threats the immune system can recognize and respond to effectively. An increase in one cell population cannot, by itself, demonstrate that a person is better protected from illness.
Growth hormone had been studied in this setting before TRIIM. A 2008 randomized trial enrolled 22 adults with HIV whose CD4 T-cell counts remained low despite antiretroviral treatment. Eleven were assigned to growth hormone plus usual HIV treatment and 11 to usual treatment alone for the first year; the comparison group could receive growth hormone in the second year. The trial was open label, so participants and treating staff knew the assignments. [2]
Thymic imaging and selected immune measures improved, but immune findings were not uniformly positive across analyses. This was evidence in people with a defined immune deficit, not a demonstration of general-population longevity benefit. The balance between potential benefit and harm can differ greatly between treating an illness and trying to improve health in people who are already well. [2]
What the original TRIIM study did
TRIIM stands for Thymus Regeneration, Immunorestoration, and Insulin Mitigation. Ten apparently healthy men aged 51–65 entered the study; nine contributed to its main analysis. For one year they received a combination of laboratory-produced (recombinant) human growth hormone, dehydroepiandrosterone (DHEA), and metformin. The latter two agents were included in an effort to limit growth hormone’s adverse effects on insulin and blood sugar control. [1]
The 2019 paper reported three different kinds of measurements:
Measurement | Reported result | What it tells us |
|---|---|---|
Thymic MRI | The fat-free tissue fraction increased significantly in seven of nine men. | Thymic composition changed; a scan alone does not establish stronger protection from illness. |
Immune-cell measurements | Selected naïve T-cell and related measures improved. Some measures of senescent T cells did not change consistently. | Selected parts of the immune-cell profile changed, with important null findings. |
DNA-methylation clocks | The average age estimate was about 1.5 years below its starting value after treatment. | A biomarker estimate changed; it was not a measurement of years of life gained. |
Naïve T cells have not yet encountered their specific target and can contribute to responses to unfamiliar threats. Senescent T cells have features associated with cellular aging. Neither label alone establishes how effectively the whole immune system works. All the table’s results come from the same small, uncontrolled pilot. [1]
Why “2.5 years younger” needs explanation
The frequently cited 2.5-year figure includes the year of chronological aging that passed during treatment. The clock estimate finished about 1.5 years below baseline; adding that elapsed year gives a 2.5-year difference relative to chronological aging. There was no separate untreated group to show how the clock would have changed without treatment. Neither number represents added lifespan. [1]
DNA-methylation clocks combine patterns of chemical marks on DNA into an estimate of age or age-related risk. They make it possible to study biological changes over months rather than wait for decades of survival follow-up. Their convenience does not make every treatment-induced change a health benefit.
The US Food and Drug Administration (FDA) distinguishes outcomes such as how people feel, function, or survive from biomarkers used as substitutes. A substitute needs evidence supporting its use in the relevant setting. A clock that predicts health outcomes in an observational population is not automatically a validated measure of a treatment’s benefit. This is a general principle, not an FDA decision about TRIIM’s clocks. [3]
For thymus research, the persuasive sequence would connect structural changes with useful immune function and then with outcomes that matter to patients. A response to vaccination or a reduction in clinically important infections, chosen as an outcome before analysis, could help test that sequence. Those are examples of future research questions, not benefits demonstrated by TRIIM.
What the uncontrolled design leaves unanswered
Before-and-after measurements can show change during treatment. They cannot fully establish what similar participants would have experienced without the intervention. Repeat testing can move an unusually high or low starting value toward its usual level. Participation may alter exercise, diet, or other behavior, while sample handling and analytical variation can affect laboratory results.
These explanations can coexist with a real treatment effect. The problem is not that every favorable finding must be an artifact, but that the study cannot reliably separate the possibilities or estimate their contributions. Random assignment to a suitable comparator, with assessors unaware of assignment where possible, would strengthen that assessment.
TRIIM also studied a combination. Even if all changes were caused by treatment, it would not reveal the contribution of growth hormone, DHEA, metformin, or their interactions. A positive combination study does not establish the effect of any component used alone.
The original trial was not registered on ClinicalTrials.gov before it began, and its analysis did not apply an overall statistical adjustment for testing many outcomes. The authors explained their reasoning, including the relationships among tests. With many measurements in nine participants, confirmation in studies with outcomes and analyses defined in advance remains important: several favorable, related measurements are not several independent trials. [1]
Durability is another open question. Additional blood testing six months after treatment was available only for the first of two recruitment cohorts. That limited follow-up does not describe what happens indefinitely after treatment ends, and a faster clock change over one part of the year cannot be projected into years of continuing rejuvenation. [1]
What TRIIM-X is designed to add
TRIIM-X, registered as NCT04375657, describes a planned 85 participants aged 40–80, including men and eligible women. The protocol specifies random assignment to growth hormone, metformin, and DHEA or to an active comparator of metformin and DHEA. The people assessing outcomes are to be kept unaware of assignment. Primary measures over 12 months are the methylation-based GrimAge estimate, thymic density, and safety. [4]
This design could help establish what adding growth hormone changes beyond the two-drug comparator. It does not compare the combination with no treatment, and the number 85 is an estimated enrollment target in the registry.
The dated status is important. At the September 22, 2026 evidence date, the registry still displayed “Recruiting,” but the last posted update was May 7, 2025. Its estimated December 2025 completion date had passed, and no results were posted there. Those fields do not establish whether enrollment was still active or whether the study had actually finished. [4]
Intervene Immune’s website describes an active program, reports encouraging immune and fitness changes, and lists 85 participants as enrolled. That sponsor statement differs from the registry’s estimated count. The website’s claims lack the complete methods, participant flow, comparative analyses, and safety dataset needed to assess a full TRIIM-X result. They therefore cannot yet supply the controlled confirmation the original pilot needs. [5]
The registry labels the study Phase 2, while the sponsor’s pipeline page describes its formal designation as a pilot study. The actual comparator, size, and endpoints are more informative than either label. Neither registration nor a phase label establishes efficacy or marketing authorization. [4] [6]
Growth hormone’s risks are part of the question
The US prescribing information for Genotropin, a somatropin product, revised in July 2026, lists adult growth hormone deficiency as its adult indication. Age-related thymus regeneration is not listed. This product label is useful safety context; it does not establish authorization of the TRIIM combination. [7]
The label warns about impaired glucose tolerance and diabetes, fluid retention, joint symptoms, and carpal tunnel syndrome, and says the product should not be used in people with active cancer. Carpal tunnel syndrome involves pressure on a nerve at the wrist and can cause hand symptoms. These risks do not disappear because the intended goal is healthier aging. [7]
TRIIM reported joint pain, fluid retention, and carpal tunnel symptoms. Two cases required dose modification. The authors described the effects as mild, but nine main participants cannot establish long-term safety or exclude uncommon harms in a larger population. [1]
There is also relevant evidence from a different regimen. In a 26-week randomized, placebo-controlled trial of 131 adults aged 65–88, growth hormone with or without sex hormones improved aspects of body composition, but strength and endurance gains were not consistent across groups. Some men receiving growth hormone with testosterone improved endurance; the women’s strength and endurance findings were not statistically significant. Fluid retention and glucose problems were among the adverse effects. [8]
That trial cannot supply TRIIM-specific event rates. It does show why changes in body composition or other biological measures must be weighed alongside function and harm. Monitoring and a limited treatment period can help manage a research study; adding drugs intended to moderate one side effect does not prove that all relevant risks have been removed.
How Healthy Longevity Clinic experts evaluate the evidence
For someone hoping to resist infections and remain well with age, the decisive distinction is between changing an immune-related measurement and improving useful immune protection. HLC treats TRIIM’s seven-of-nine MRI response as a meaningful reason for further study, while keeping the selected immune findings, null results, and clock arithmetic in their proper roles. None measures whether participants became less likely to develop serious illness. [1]
In a clinical conversation, a younger clock score should lead to a more specific question: what health outcome is expected, and has this exact combination improved it compared with an appropriate alternative? The answer must also account for glucose effects, fluid retention, and other known hormone risks. A strategy meant to support immunity may have an unfavorable balance if it changes a score without improving health. [1] [7] [8]
Complete TRIIM-X group comparisons could clarify the contribution of adding growth hormone to metformin and DHEA. Confidence in preventive use would need more: durable, clinically useful immune outcomes, full reporting of harms, and independent confirmation in an applicable population. That is the route from an interesting organ-level result to a decision relevant to healthy aging.
What to look for in the next complete report
A useful report would show the differences between assigned groups and the uncertainty around them, using endpoints specified before analysis. It would account for every participant, including withdrawals and missing measurements, and give adverse events the same attention as favorable findings.
Statistical significance and practical importance need separate answers. A larger trial can estimate a difference more reliably, but it still answers only the questions its outcomes measure. Longer follow-up and independent replication would help establish whether any effect lasts and applies beyond the original selected participants.
TRIIM supports continued investigation of thymus regeneration. Controlled evidence of infection prevention and acceptable risks is still needed before the combination could support routine preventive treatment.
Three questions for a clinical conversation
Does the proposed benefit concern thymic imaging, immune-cell measurements, a clock score, or fewer clinically important illnesses?
What does the comparison group allow the study to establish about growth hormone’s added effect?
How are known hormone risks and longer-term adverse effects weighed against the specific benefit being proposed?
Common questions
Did TRIIM make participants 2.5 years younger?
That figure describes clock arithmetic relative to the year of chronological aging that elapsed. The average estimate was about 1.5 years below baseline, without a measured untreated comparison. It does not mean that participants gained 2.5 years of life. [1]
Does less thymic fat mean stronger immunity?
It is evidence of a structural change. Useful immune function and protection from illness require their own evidence; the study’s imaging and selected immune-cell changes did not demonstrate fewer infections or cancers. [1]
Is a registered Phase 2 trial an approved treatment?
No. Registration describes a research study. TRIIM-X’s active comparator and outcomes define what it can test; its registry label is not proof of efficacy or authorization for routine preventive treatment. [4] [6]
What remains uncertain
The original small, uncontrolled combination study cannot establish causality or component-specific benefit. Lack of preregistration, multiple comparisons, and additional six-month follow-up available only for the first recruitment cohort weaken certainty. Sponsor statements of enrollment and favorable changes do not supply complete comparative methods, participant flow, or safety results. The stale registry does not confirm current recruitment or actual completion. Imaging, immune markers, and clocks do not establish disease prevention. Original adverse effects and established somatropin risks require careful benefit–harm assessment.
References
- Reversal of epigenetic aging and immunosenescent trends in humans
- Growth hormone enhances thymic function in HIV-1–infected adults
- Surrogate Endpoint Resources for Drug and Biologic Development
- TRIIM-X, NCT04375657
- The Science; Our Programs
- Our Pipeline
- Genotropin (somatropin) US prescribing information
- Growth hormone and sex steroid administration in healthy aged women and men: a randomized controlled trial
- Longevitytech.fund. Official portfolio, checked September 26, 2026.
Disclosure
Prepared with AI assistance. The 2019 TRIIM paper disclosed that four authors held shares or options in Intervene Immune, and two were company officers named in a related patent application. Intervene Immune supported the study and provides the sponsor webpages discussed here. These interests make transparent methods and independent confirmation valuable; they do not, by themselves, invalidate the findings. [1,5,6] Longevitytech.fund lists Intervene Immune in its official investment portfolio.